Curbside Consult Thread

Collapse
X
 
  • Time
  • Show
Clear All
new posts
  • Viking
    Banned
    • Jun 2009
    • 6470

    #61
    Originally posted by CardiacCoug View Post
    That doesn't sound like something that really happens.

    You can get clot in the left atrial appendage (in the setting of atrial fibrillation) but that's almost impossible to see on a surface echo. Other atrial masses visible on a surface echocardiogram are almost always myxomas rather than thrombus. There is an entity known as an interatrial septal aneurysm but these don't contain clot. Otherwise there really isn't such a thing as an "atrial aneurysm". Is it an aortic aneurysm?

    Your patient needs a TEE and a more reasonable diagnosis unless I am missing something. Maybe they can do bypass surgery and remove the 4 cm thrombus or myxoma while they are at it.
    That seems like an important detail. But I'm not a doctor, dammit.

    Comment

    • doctorcoug
      To Win is to Honor Him
      • Jun 2009
      • 2273

      #62
      Originally posted by CardiacCoug View Post
      That doesn't sound like something that really happens.

      You can get clot in the left atrial appendage (in the setting of atrial fibrillation) but that's almost impossible to see on a surface echo. Other atrial masses visible on a surface echocardiogram are almost always myxomas rather than thrombus. There is an entity known as an interatrial septal aneurysm but these don't contain clot. Otherwise there really isn't such a thing as an "atrial aneurysm". Is it an aortic aneurysm?

      Your patient needs a TEE and a more reasonable diagnosis unless I am missing something. Maybe they can do bypass surgery and remove the 4 cm thrombus or myxoma while they are at it.
      When the cardiologist called me to report the findings I said, "he's had anginal symptoms" to which he said "why don't you send him over to me today"? I replied, "sure" but was thinking, "um, ya think"!

      I'll let you know what comes of it all. I don't have access to the echo images, just the report.
      "Don't expect I'll see you 'till after the race"

      "So where does the power come from to see the race to its end...from within"

      Comment

      • ERCougar
        Junior Member
        • Nov 2008
        • 10978

        #63
        75 yo man brought in by EMS after being found by his neighbor unconscious on his front porch. On arrival, BG is 19. They get an IV and give him an amp of D50, so by the time I see him, he's awake and alert. And pissed.

        Turns out, this guy has very explicit DNR orders that forbid anything being done (even IVs). He's also a diabetic on an insulin pump who cranked it up, took some extra Lantus, a bunch of Percocet, and didn't eat, in a suicide attempt. So now his BG is (temporarily) fine, as he is on a D10 drip that he's now refusing and is threatening to charge me with assault if I don't turn it off immediately. Family members have also arrived and are just as pissed ("why bother to fill these out if you're just going to ignore them?", the brother asks). He's suicidal and I guess could be concerned incompetent by that standard, but I have to assume he was competent when he filled out the DNR, and beyond that, his brother, who is the legal POA, is also therefore his surrogate decision maker. So I feel like I have no choice but to shut off the drip and watch him die.

        We had gotten the hospital ethics committee involved and when they find out I shut off the drip, they say that it's illegal to assist in a suicide and advise me to turn it back on. At this point, the guy is again comatose and his POA is telling me that he's going to charge me with assault if I ignore the DNR papers. So what do you do?

        A couple of thoughts:
        1) The guy is old and in poor health at baseline. so there is nothing suspicious about him having a DNR or the POA supporting that DNR.
        2) If we resuscitate the guy, remember that he's also ingested a bunch of acetaminophen, and levels were to the point of buying an acetylcysteine course, and in being in real danger of going into hepatic failure anyway. So we resuscitate him from a relatively peaceful hypoglycemic to a miserable liver failure one a few days later. Family will not be pleased.
        At least the Big Ten went after a big-time addition in Nebraska; the Pac-10 wanted a game so badly, it added Utah
        -Berry Trammel, 12/3/10

        Comment

        • hostile
          lollygagger
          • Dec 2009
          • 5736

          #64
          Originally posted by ERCougar View Post
          75 yo man brought in by EMS after being found by his neighbor unconscious on his front porch. On arrival, BG is 19. They get an IV and give him an amp of D50, so by the time I see him, he's awake and alert. And pissed.

          Turns out, this guy has very explicit DNR orders that forbid anything being done (even IVs). He's also a diabetic on an insulin pump who cranked it up, took some extra Lantus, a bunch of Percocet, and didn't eat, in a suicide attempt. So now his BG is (temporarily) fine, as he is on a D10 drip that he's now refusing and is threatening to charge me with assault if I don't turn it off immediately. Family members have also arrived and are just as pissed ("why bother to fill these out if you're just going to ignore them?", the brother asks). He's suicidal and I guess could be concerned incompetent by that standard, but I have to assume he was competent when he filled out the DNR, and beyond that, his brother, who is the legal POA, is also therefore his surrogate decision maker. So I feel like I have no choice but to shut off the drip and watch him die.

          We had gotten the hospital ethics committee involved and when they find out I shut off the drip, they say that it's illegal to assist in a suicide and advise me to turn it back on. At this point, the guy is again comatose and his POA is telling me that he's going to charge me with assault if I ignore the DNR papers. So what do you do?

          A couple of thoughts:
          1) The guy is old and in poor health at baseline. so there is nothing suspicious about him having a DNR or the POA supporting that DNR.
          2) If we resuscitate the guy, remember that he's also ingested a bunch of acetaminophen, and levels were to the point of buying an acetylcysteine course, and in being in real danger of going into hepatic failure anyway. So we resuscitate him from a relatively peaceful hypoglycemic to a miserable liver failure one a few days later. Family will not be pleased.
          Man that's tough. Can you give the guy an amp of D50 to get his blood sugar normal and have the family/POA sign him out? Couldn't they just sign him out AMA without you doing anything further?
          "You interns are like swallows. You shit all over my patients for six weeks and then fly off."

          "Don't be sorry, it's not your fault. It's my fault for overestimating your competence."

          Comment

          • ERCougar
            Junior Member
            • Nov 2008
            • 10978

            #65
            Originally posted by hostile View Post
            Man that's tough. Can you give the guy an amp of D50 to get his blood sugar normal and have the family/POA sign him out? Couldn't they just sign him out AMA without you doing anything further?
            We had two problems with that. First, the family left early because they "didn't want to watch him die" (although it was clearly his wish--yeah, I'm as confused by that as you are). We obviously can't let a suicidal patient sign himself out. Second, when the brother returned and we had turned back on the drip (per Ethics committee instruction--yes, that's what I decided to do), the admitting physician convinced the brother that we were legally obligated to save him as he had attempted to commit suicide. Whether the brother remains convinced as he watches him die from fulminant hepatic failure is a different question. I'm not convinced that he or the ethics committee read the situation correctly but I'm only at this hospital for a few days a month (and I'm not sure I'm right either) so I just went along.
            At least the Big Ten went after a big-time addition in Nebraska; the Pac-10 wanted a game so badly, it added Utah
            -Berry Trammel, 12/3/10

            Comment

            • doctorcoug
              To Win is to Honor Him
              • Jun 2009
              • 2273

              #66
              Originally posted by ERCougar View Post
              fulminant hepatic failure
              Hospice consult!

              That is a very difficult situation. Good job for getting the emergent ethics committee. Also, very good to get the PCP involved, as he/she likely has a different relationship with the family.
              "Don't expect I'll see you 'till after the race"

              "So where does the power come from to see the race to its end...from within"

              Comment

              • doctorcoug
                To Win is to Honor Him
                • Jun 2009
                • 2273

                #67
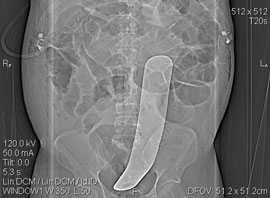
                Surgeons:

                This will ruin your day:


                Kinda makes you want to do the count yourself. res ipsa loquitur? The nurse isn't on the hook nor his/her employer, but the surgeon.
                "Don't expect I'll see you 'till after the race"

                "So where does the power come from to see the race to its end...from within"

                Comment

                • Viking
                  Banned
                  • Jun 2009
                  • 6470

                  #68
                  Originally posted by doctorcoug View Post
                  Surgeons:

                  This will ruin your day:


                  Kinda makes you want to do the count yourself. res ipsa loquitur? The nurse isn't on the hook nor his/her employer, but the surgeon.
                  Sheesh, that's a grotesquely gigantic Johnson. Please don't post that stuff here, ok?

                  Comment

                  • San Juan Sun
                    Kicked to the curb
                    • Dec 2009
                    • 9214

                    #69
                    Originally posted by doctorcoug View Post
                    Surgeons:

                    This will ruin your day:


                    Kinda makes you want to do the count yourself. res ipsa loquitur? The nurse isn't on the hook nor his/her employer, but the surgeon.
                    A couple of my trainers have been sued for retained objects. Even the residents assisting in the case were named, in one instance. Not very fun. In both cases, they were supposedly told by the circulating nurse that the instrument counts were correct.
                    "Sure, I fought. I had to fight all my life just to survive. They were all against me. Tried every dirty trick to cut me down, but I beat the bastards and left them in the ditch."

                    - Ty Cobb

                    Comment

                    • hostile
                      lollygagger
                      • Dec 2009
                      • 5736

                      #70
                      Originally posted by doctorcoug View Post
                      Surgeons:

                      This will ruin your day:


                      Kinda makes you want to do the count yourself. res ipsa loquitur? The nurse isn't on the hook nor his/her employer, but the surgeon.
                      Until recently, counts only consisted of sponges and needles. Cases like this, however, have caused hospitals to institute counting instruments as well. Also, getting an xray in the OR, before waking the patient, has become more common. I'd bet the hospital is likely "on the hook" as it is the nurse who initiates and verifies that the counts are correct.
                      "You interns are like swallows. You shit all over my patients for six weeks and then fly off."

                      "Don't be sorry, it's not your fault. It's my fault for overestimating your competence."

                      Comment

                      • doctorcoug
                        To Win is to Honor Him
                        • Jun 2009
                        • 2273

                        #71
                        Originally posted by hostile View Post
                        Until recently, counts only consisted of sponges and needles. Cases like this, however, have caused hospitals to institute counting instruments as well. Also, getting an xray in the OR, before waking the patient, has become more common. I'd bet the hospital is likely "on the hook" as it is the nurse who initiates and verifies that the counts are correct.
                        This was at S&W, who supposedly used to x-ray all bellies post op.
                        "Don't expect I'll see you 'till after the race"

                        "So where does the power come from to see the race to its end...from within"

                        Comment

                        • hostile
                          lollygagger
                          • Dec 2009
                          • 5736

                          #72
                          Originally posted by doctorcoug View Post
                          This was at S&W, who supposedly used to x-ray all bellies post op.
                          Then the hospital administrator and chief of surgery will get to explain why they discontinued the practice.
                          "You interns are like swallows. You shit all over my patients for six weeks and then fly off."

                          "Don't be sorry, it's not your fault. It's my fault for overestimating your competence."

                          Comment

                          • doctorcoug
                            To Win is to Honor Him
                            • Jun 2009
                            • 2273

                            #73
                            Originally posted by hostile View Post
                            Then the hospital administrator and chief of surgery will get to explain why they discontinued the practice.
                            I know laps are not your arena. I'm new to medicine, however. Was the post op X-ray common? Is it becoming common? Any evidence? SJS?
                            "Don't expect I'll see you 'till after the race"

                            "So where does the power come from to see the race to its end...from within"

                            Comment

                            • Danimal
                              Junior Member
                              • May 2009
                              • 387

                              #74
                              A 20 something year old admitted to inpatient psychiatry who was suicidal and with unusual cognitive presentation. Neuropsych testing from a few years ago was completely normal. Now, his response time for even the most basic closed question is several questions. Brain is completely fried. Likely going to need nursing home care. The cause: less than a year of huffing.

                              Inhalants are bad news.

                              Comment

                              • risicam
                                BYU loving Realtor
                                • Mar 2012
                                • 144

                                #75
                                Originally posted by Danimal View Post
                                A 20 something year old admitted to inpatient psychiatry who was suicidal and with unusual cognitive presentation. Neuropsych testing from a few years ago was completely normal. Now, his response time for even the most basic closed question is several questions. Brain is completely fried. Likely going to need nursing home care. The cause: less than a year of huffing.

                                Inhalants are bad news.
                                Wow...so sad!

                                Comment

                                Working...